OpenEvidence

Screenshots



Details
- Rating
- 146.00 reviews
- Version
- 2.9.25
- Developer
- OpenEvidence
Analysis by Norviv
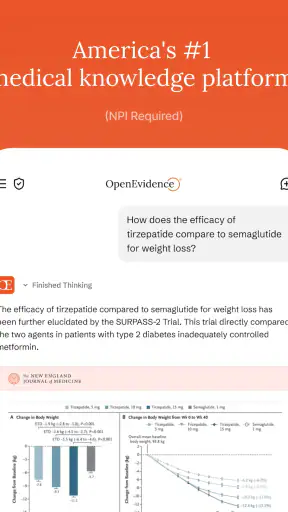
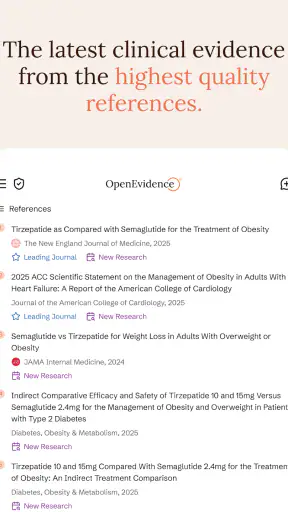
OpenEvidence is a medical app from OpenEvidence that I would describe as a point-of-care reference rather than a general health tool. Its purpose is to help eligible users look for accurate answers while working through a clinical question, and that distinction matters from the first screen. This is not the kind of app I would install for symptom browsing, casual wellness advice, or a second opinion about a personal diagnosis. It is aimed at professional use, and access depends on an NPI.
I approached it as something a clinician might keep available during a busy day: not a replacement for training, judgment, or local protocols, but a way to get oriented when a question needs a focused answer. In that role, the app feels more useful than a broad web search because the intention is clearer. Instead of sorting through general pages, I can frame a clinical question and use the response as a starting point for checking the relevant evidence and deciding what to do next.
The most important point is that OpenEvidence should support clinical reasoning, never stand in for it. That sounds obvious, but it changes how I use the app. I treat an answer as a research aid that needs context, especially when the patient has several conditions, unusual findings, medication risks, or an urgent presentation. Used with that discipline, it can reduce the time spent getting from a question to a useful direction.
Where the first-use friction usually appears
The first obstacle is not learning a complicated interface. It is understanding who the app is for. The store summary makes the NPI requirement explicit, so a person without the required professional identifier should not expect a normal consumer sign-up experience. If you are a patient looking for a diagnosis or a family member trying to interpret a symptom, this is probably the wrong download, even though the content rating is Everyone.
That age label can be misleading if read without context. Everyone describes the store classification, not the intended clinical audience or the suitability of the answers for self-treatment. I would not use the app to decide whether to start, stop, or change a medicine for myself. A general medical website, a licensed clinician, or an urgent care service is more appropriate for those situations.
For an eligible user, the next point of friction is identity and access. I would have the NPI details ready before beginning, use the same professional information consistently, and avoid treating a failed sign-in as proof that the app itself is broken. A mistyped identifier, an incomplete account step, or a mismatch in professional details can all stop progress before the app’s clinical usefulness is even tested.
There is also a practical difference between an app that answers questions and a database that lets me browse a fixed collection of references. OpenEvidence is more conversational in spirit: I need to ask a well-formed question. That can feel slower than typing a short phrase into a familiar search engine at first, but the payoff is that the question can be shaped around the clinical decision rather than a loose keyword.
Stories Picked for You

Life360 Works Better When Your Household Agrees on What to Share

YouVersion Bible Fits Scripture into Everyday Phone Routines

Matchington Mansion Review: Match-Three Puzzles With a Place to Restore
Android Auto Shows Why Safer Driving Software Does Less
Google Find Hub Runs on Shared Devices and Quiet Trust

Sygic GPS Navigation: The Ultimate Offline Travel Companion
I found that vague prompts are the easiest way to get an unsatisfying result. “Pneumonia treatment” is much less useful than a question that identifies the patient context, the decision I am trying to make, and the relevant limitation. I would include the setting, important comorbidities, the suspected diagnosis, and the point that needs clarification. The app cannot compensate for a missing clinical frame.
What to check before blaming the app
Before using it in a real workflow, I would confirm that the device meets the minimum operating requirement. The current release is version 2.9.25, and the app supports Android 7.0 or later. That makes compatibility fairly broad, but an older phone can still produce a poor experience if the operating system is outdated, storage is tight, or the device is struggling with other applications.
I would also update the app through the normal store process rather than relying on an old installation. OpenEvidence was released on October 1, 2024, and its current version is the one I would want to test before deciding whether a problem is persistent. If the app opens but behaves strangely, closing it fully and reopening it is a sensible first step. If that does not help, restarting the device can clear a temporary system issue without changing account information.
Connection quality deserves an early check. A clinical answer is not something I want to request while moving between weak signals and then assume the empty or stalled result is a content problem. I would switch to a more stable connection, retry once, and avoid repeatedly submitting the same question. Repeated taps can create confusion about whether a request is still processing or whether several requests were sent.
My setup checklist would be simple:
- Confirm that the device runs Android 7.0 or newer.
- Make sure the app is updated to the current release.
- Have the required NPI information available.
- Use a stable connection before sending an important question.
- Prepare a concise clinical question instead of starting with a single broad keyword.
These steps are not glamorous, but they prevent a common mistake: judging the medical usefulness of the app while the real issue is access, compatibility, or connectivity. I would also avoid testing it for the first time during a time-critical decision. A new tool needs a calm trial run so I can learn its response style and understand how it fits beside the resources I already trust.
How I would recover a stalled workflow
If a question does not return a useful answer, my first response would be to improve the question rather than immediately assume the service failed. I would remove unnecessary wording, state the exact decision, and add only the patient details that change the interpretation. For example, instead of asking for every possible cause of a symptom, I would ask about the differential diagnosis in a defined context and identify the finding that is causing uncertainty.
This is one of the more important practical insights with a question-based medical tool: a second attempt should not merely repeat the first. I would change the structure. Put the clinical setting first, the suspected problem second, and the decision point last. If the question involves treatment, I would include the factors that affect safety, such as relevant organ impairment, allergies, pregnancy status, or interacting medicines when those details are known and appropriate to the task.
I would also separate exploration from confirmation. In the first pass, I might ask for the main considerations and the evidence behind them. In the next pass, I would narrow the question to the specific issue that remains unresolved. That workflow is more reliable than asking one enormous question and treating the response as a complete consultation.
When the interface appears unresponsive, I would use a short recovery sequence: wait briefly, check the connection, close and reopen the app, then retry with a shorter prompt. If access itself is failing, I would revisit the NPI and account details rather than repeatedly changing the clinical wording. Keeping those two problems separate makes troubleshooting much faster.
A useful habit is to keep an independent route to trusted clinical references available. OpenEvidence can help me orient myself, but I would still verify a high-stakes conclusion against the appropriate guideline, formulary, institutional policy, or primary source. If the app gives an answer that conflicts with a known protocol, that conflict is a reason to investigate, not a reason to choose whichever answer is more convenient.
I would be especially careful with copied patient information. The safest workflow is to ask a focused, de-identified question and avoid unnecessary personal details. The app’s value comes from the clinical problem and its relevant context, not from including identifying information. That also makes the prompt easier to read and the answer easier to apply.
When the app is not the cause of the problem
Sometimes the difficulty is the question itself. Clinical language is full of terms that can mean different things depending on the setting, and a short prompt may leave too much room for interpretation. If the answer feels generic, I would ask whether I supplied enough context to distinguish an outpatient question from an emergency presentation, or a first-line decision from a treatment failure.
Sometimes the limitation is the decision. No answer tool can resolve uncertainty that requires an examination, imaging, laboratory results, specialist input, or direct discussion with the patient. If the available facts are incomplete, the right next step may be gathering better information rather than requesting a more confident answer. OpenEvidence can help organize the question, but it cannot perform the missing clinical work.
There are also cases where a local source is better. Medication availability, hospital pathways, referral rules, and institutional procedures may differ from broad medical evidence. For those questions, I would use the relevant local policy or pharmacist alongside the app. A concise answer from OpenEvidence may be useful background, but it should not override a current local requirement.
I would skip OpenEvidence entirely for personal health decisions if I were not an eligible professional. The free price makes it easy to try, but free access does not turn a professional reference into a consumer diagnostic service. It is also not the best choice for someone who wants a symptom tracker, appointment manager, medication reminder, or a simple patient education library. Its value is concentrated in answering clinical questions at the point of care.
Even for clinicians, I would not make it the only resource for rare, rapidly changing, or exceptionally high-risk cases. A focused answer can save time, but speed is not the same as completeness. When the consequences of a mistake are serious, I would use the app to generate or refine questions and then confirm the result through the sources and colleagues appropriate to that case.
How it compares with familiar medical alternatives
Compared with a general search engine, OpenEvidence offers a more clinically directed starting point. A web search can be useful when I already know the exact guideline, organization, or paper I want, but it also produces a mixture of professional and consumer material. The app is more appealing when the task is to frame a clinical question quickly without sorting through unrelated results.
Compared with a traditional reference database, the advantage is the question-first workflow. A database is often better when I want to browse a known topic systematically, inspect a full monograph, or follow a citation trail in detail. OpenEvidence is more convenient when I have a defined uncertainty and need an initial synthesis to guide the next search.
Compared with asking a colleague, it is available without interrupting someone else, which is valuable during a crowded shift. But a colleague understands local practice, the patient’s history, and the practical constraints in a way an app cannot. I see the strongest workflow as complementary: use OpenEvidence to sharpen the issue, then involve a human expert when the case needs judgment, experience, or accountability.
The trade-off is therefore clear. The app can make the first step faster, but it does not remove the need for source checking. It is strongest as a focused clinical companion and weakest when someone expects a complete, individualized decision without supplying context or applying professional judgment.
Who will get the most from it
I think OpenEvidence is best suited to eligible clinicians, trainees working under supervision, and healthcare professionals who regularly need to clarify a medical question while caring for patients. A realistic example would be a clinician between appointments who remembers the broad issue but wants to organize the evidence around a treatment choice. Rather than opening several unrelated browser tabs, they can formulate the question, review the response, and then check the conclusion against the resources required by their workplace.
For a trainee, the learning value is not just the answer. Rewriting a vague question into a focused one exposes what information is missing and what decision is actually being made. I would use it as a prompt for further study, then compare the response with teaching materials or supervision. That approach turns the app into a reasoning aid rather than a shortcut around learning.
The app’s public numbers also suggest that it has reached a substantial audience: it has over 500 thousand installs, an average rating of 4.9 from around 4.5 thousand ratings, and 146 written reviews. I would treat those figures as encouraging signs of interest, not proof that every answer will fit every specialty or workflow. A strong rating cannot replace my own trial with the cases and references I handle.
It is free to install and carries an Everyone content rating, which lowers the barrier to exploring it. Still, the NPI requirement remains the practical gatekeeper. That combination makes it easy for a professional to test, but it should not invite casual use by people looking for personal medical advice.
My practical verdict after using it
I would recommend OpenEvidence to an eligible medical professional who wants a fast, focused way to begin investigating a clinical question. The app makes the most sense when I use it early in the reasoning process: define the problem, ask a precise question, inspect the answer critically, and verify anything that could affect patient safety. That workflow is more valuable than simply treating the app as an answer box.
I would not recommend it as a standalone diagnostic authority, a replacement for local guidance, or a consumer symptom checker. Its setup can also frustrate users who overlook the NPI requirement, and its usefulness depends heavily on the quality of the prompt and the context supplied. Those are not minor details; they determine whether the experience feels efficient or disappointing.
My final view is positive but deliberately measured. OpenEvidence gives clinicians a practical way to turn a moment of uncertainty into a structured research step, and its free availability makes that experiment easy for the right audience. If you approach it with a stable setup, a well-framed question, and a habit of checking high-stakes conclusions, I think it can earn a place beside—not instead of—the medical references and human expertise you already rely on.
Frequently Asked Questions
01What is OpenEvidence, and who is it designed for?
OpenEvidence is an AI-powered medical information platform designed primarily for healthcare professionals, students, and other users who need quick access to evidence-based clinical knowledge. It can help summarize medical topics, answer clinical questions, and point users toward supporting sources. It should be treated as a research and decision-support tool rather than a replacement for professional training, clinical judgment, institutional policies, or consultation with qualified specialists.
02Can OpenEvidence be used to diagnose patients or recommend treatments?
OpenEvidence may provide useful medical explanations and information related to symptoms, conditions, tests, and treatments, but it should not be relied on as an autonomous diagnostic or prescribing system. AI-generated answers can be incomplete, outdated, or misinterpreted, especially in complex cases. Healthcare professionals should verify important details against trusted medical references and use their own clinical judgment before making decisions about patient care.
03How reliable are the answers and medical sources provided by OpenEvidence?
The platform is intended to deliver evidence-based responses, often with references or explanations that help users investigate a topic further. However, no AI medical tool is perfect. Answers may contain errors, omit relevant context, or fail to reflect the newest guidelines. Before acting on any response, check the cited material, confirm publication dates, consider the patient’s circumstances, and compare the information with authoritative guidelines or approved clinical resources.
04Is patient or personal health information safe to enter into OpenEvidence?
Users should be careful when entering information into any online medical application, including OpenEvidence. Avoid submitting names, addresses, medical record numbers, photographs, or other details that could identify a patient unless the service, your organization, and applicable privacy requirements clearly permit it. Review the platform’s current privacy policy, terms of use, and data-handling practices before use, particularly when working with confidential clinical information.
05Is OpenEvidence free, and what do I need to use it?
Access and available features may depend on the current OpenEvidence plan, eligibility requirements, region, and whether the service is offered through an institution or professional account. Some users may need to register, verify their professional status, or sign in through an approved organization. Because pricing, access rules, and supported devices can change, check the official OpenEvidence website or app-store listing before downloading or relying on a specific feature.


